Regeneron recently gave away a gene therapy, not to generate goodwill, but because the reimbursement system could not support payment for an approved treatment. That decision illustrates the central problem in medical innovation: scientific progress is no longer the main constraint. The real bottleneck now sits in the systems meant to deliver these advances.
The Science Has Already Arrived
More than 39 cell and gene therapies have US regulatory approval, with over 80 projected by 2032. CAR-T therapies have delivered outcomes in oncology that exceed standard treatments. Gene replacement therapies for rare diseases have produced durable, sometimes curative, results after a single administration. The evidence is clear: these are major advances. Most payers now accept that cell and gene therapies are clinically effective. The question of whether the science works is no longer the main point of contention.
The unresolved issue, and the one that matters most for healthcare leadership, is whether manufacturing, clinical site capacity, reimbursement, and financing can reliably deliver approved therapies to patients.
A Capacity Problem That Isn't Improving
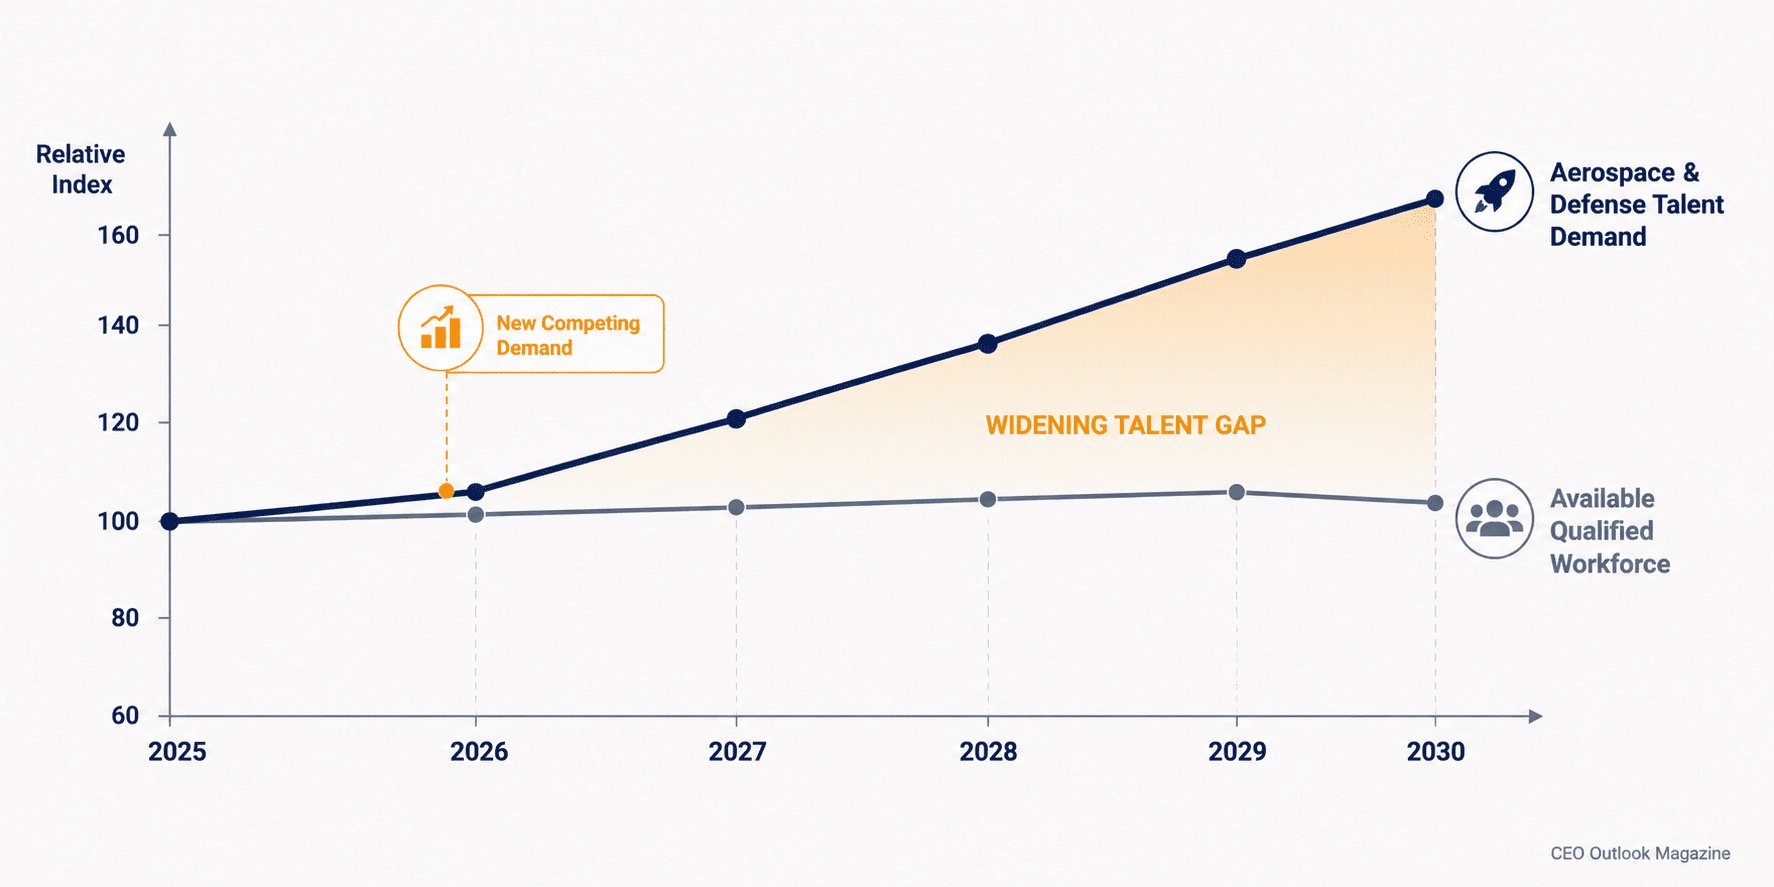
Delivering advanced cell or gene therapies is fundamentally different from dispensing conventional drugs. Each dose is often made for a single patient, resulting in fragile, low-throughput supply chains and significant operational strain on clinical sites. Providers must hold intensive care capacity, keep clinical teams on standby, and manage unstable patients for extended periods while waiting for therapy delivery, because manufacturing and logistics remain unpredictable. Today, only large, well-resourced centers can absorb that risk. Clinical site capacity has become a structural constraint on patient access, and the data shows little progress: the number of qualified treatment centers in the US did not increase between 2024 and 2025, even as approvals and demand rose. Different Kind of Medicine
The more fundamental mismatch is in payment systems. Traditional healthcare financing looks at cost and benefit over short, usually annual, periods. Cell and gene therapies reverse this: a single treatment can require a large upfront payment but deliver benefit over many years, sometimes a lifetime. This cost-density problem is now the most frequently cited barrier to broader access. Seventy-nine percent of payers point to reimbursement complexity as the main obstacle to scaling these therapies, even as they accept the science.
The practical consequences show up directly at the point of care. Reimbursement delays following CAR-T administration have an immediate impact at the point of care. Reimbursement delays after CAR-T administration create real financial risk for hospitals. Smaller institutions may limit the number of CAR-T patients they treat each month or wait for reimbursement before accepting new cases. After a new therapy is approved, most payers—58 percent in one survey—say they are only moderately to extremely likely to cover it under miscellaneous billing codes, a temporary solution never intended for therapies expected to become standard practice. Possible in recent acquisition activity. Eli Lilly's move to acquire Orna Therapeutics for up to US$2.4 billion, followed by its acquisition of Kelonia Therapeutics for up to US$7 billion, both targeted technology designed to generate cell therapy directly inside a patient's body, eliminating much of the external manufacturing and logistics complexity that currently constrains delivery. These are not bets on discovering more effective science. They are bets on solving the delivery system itself, because the industry has concluded that removing the manufacturing and logistics bottleneck may be worth more than the next incremental gain in therapeutic efficacy.
What This Means for Healthcare Leadership
For hospital executives, payers, and life sciences leaders, the implication is direct: investment in research and development must now be matched by investment in delivery infrastructure, expanded clinical site capacity, financing structures that reflect durable one-time value rather than annual cost cycles, and reimbursement pathways that do not leave hospitals carrying financial risk while payment systems lag. Innovative payment models, including risk-sharing and outcomes-based arrangements, are emerging to address this mismatch, but most are still early-stage and depend on having clear, measurable outcome data.
Organizations that invest in delivery infrastructure as seriously as in science will be the ones turning medical breakthroughs into patient outcomes. Those that do not will continue to develop therapies that work in theory but remain inaccessible to the patients who need them.
How is your organization thinking about the infrastructure required to deliver medical innovation at scale, not just develop it? CEO Outlook Magazine: Most organizations focus on developing medical innovation, but far fewer have a clear plan for delivering it at scale. The question is not whether the science works, but whether the infrastructure is ready to support it.